
Peer review process
Revised: This Reviewed Preprint has been revised by the authors in response to the previous round of peer review; the eLife assessment and the public reviews have been updated where necessary by the editors and peer reviewers.
Read more about eLife’s peer review process.Editors
- Reviewing EditorKenneth HoGarvan Institute of Medical Research, Darlinghurst, Australia
- Senior EditorDolores ShobackUniversity of California, San Francisco, San Francisco, United States of America
Reviewer #1 (Public review):
This work evaluates the impact of reproductive history on growth, body weight and body composition in mammals. In mice, somatic growth is stimulated by the first pregnancy while the second pregnancy increases body weight mainly by increasing adiposity. To probe the role of pituitary growth hormone (GH), the key regulator of somatic growth in these processes, this was addressed by comparing the impact of reproduction on growth in normal ("wild type") and genetically GH-deficient females and by detailed characterization of the profile of fluctuations in circulating GH levels in both types of animals. Additional studies addressed the possible role of other endocrine pathways (ghrelin and estrogen) in the pregnancy-related growth. Surprisingly, reproduction-related growth was independent of GH, ghrelin and estrogen. To determine whether these results may apply ("translate") to human physiology, data on various parameters of somatic growth were collected from women with hereditary GH deficiency. The findings indicate that GH-independent stimulation of growth by reproductive events also occurs in women.
Use of multiple animal models, rigorous characterization of GH levels in normal and GH-deficient females, and inclusion of data derived from a unique and well-characterised population of people with hereditary isolated GH deficiency and no GH replacement therapy are important strengths of these elegant and innovative studies. The results address a broader and clinically significant issue of permanent changes in body size, composition and function that result from pregnancy and lactation. This work also provides important background for further studies aimed at the identification of the mechanism involved and the role of specific reproductive events in the regulation of growth.
Reviewer #2 (Public review):
This manuscript describes the fascinating phenomenon of growth hormone (GH)-independent growth occurring in the mother during pregnancy. This growth was most pronounced in dwarf mice that are lacking the receptor for growth hormone-releasing hormone (GHRH) and therefore showing isolated GH deficiency. However, the pregnancy-induced growth could also be observed in wild-type mice, suggesting that it is a normal part of the maternal adaptation to pregnancy. The study falls short of identifying the mechanism(s) driving this pregnancy-induced growth response, but it certainly reveals a novel insight into maternal physiology. The authors have completed a range of experiments in mice to prove that, as well as being GH independent, the pregnancy-induced growth also did not require GH signaling in the liver (i.e., not another pregnancy-specific ligand operating through the GHR to promote IGF). They also provided complementary data from a population of humans with untreated isolated GH deficiency that are broadly consistent with the hypothesis. While it is important to consider the significant species differences between rodents and humans, both in terms of growth physiology and also in terms of evolution of placental somato-mammotrophic hormones, this unique population is a valuable resource and adds credence to the study. Overall, I find this a compelling research story, but somewhat unfinished. There are some areas where additional information could improve the ability to interpret the data, and some additional concepts that could be considered in the discussion. There are also areas where additional experiments might provide important insights. However, I think that such suggestions can be considered as appropriate for future research, rather than delaying the dissemination of the findings in the current manuscript.
Reviewer #3 (Public review):
Summary:
The study describes an increase in body growth and body composition in both mice and women. In mice, the impact on growth is mainly seen during the first pregnancy, and the changes postpartum on body composition are also different during the first and second pregnancies. The study has used various knockout models in the growth hormone axis to understand these changes as well as some gene expression analysis related to GH, IGF-1 and estrogen signalling pathways.
Strengths:
(1) The inclusion of various knock-out mouse models that allow for exploration of mechanisms related to the above-mentioned changes.
(2) The investigation of gene expression of GHR, IGF-1R and ER pathways.
Author response:
The following is the authors’ response to the original reviews.
eLife Assessment:
This important study reports a novel phenomenon of maternal growth during pregnancy that is independent of growth hormone (GH), adding a new dimension to maternal biology of reproduction. The evidence is convincing and supported by state-of-the-art methodologies conducted in mice and persuasive observations in humans with hereditary isolated GH deficiency. Revised discussion should focus on possible mechanisms, including the role of IGF2, and on directions for future research.
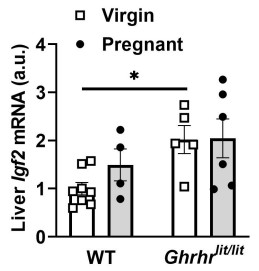
We thank the editors for these valuable suggestions. In response, we assessed hepatic Igf2 mRNA expression. As shown in Author response image 1, hepatic Igf2 mRNA expression was higher in Ghrhrlit/lit mice but was not significantly affected by pregnancy. However, we recognize that IGF-2 is produced by multiple tissues, particularly at the maternal-fetal interface, as well as by other maternal tissues, exerting endocrine or paracrine effects. Therefore, we believe that hepatic Igf2 expression alone provides only a limited view of the potential contribution of IGF-2 to the maternal adaptations induced by pregnancy. For this reason, we chose not to include these data in the revised manuscript. Instead, we expanded the Discussion to address the potential role of IGF-2 in the observed phenotypes and to highlight important directions for future research, as suggested.
Author response image 1.
Public Reviews:
Reviewer #1 (Public review):
This work evaluates the impact of reproductive history on growth, body weight and body composition in mammals. In mice, somatic growth is stimulated by the first pregnancy while the second pregnancy increases body weight mainly by increasing adiposity. To probe the role of pituitary growth hormone (GH), the key regulator of somatic growth in these processes, was addressed by comparing the impact of reproduction on growth in normal ("wild type") and genetically GH-deficient females and by detailed characterization of the profile of fluctuations in circulating GH levels in both types of animals. Additional studies addressed the possible role of other endocrine pathways (ghrelin and estrogen) in the pregnancy-related growth. Surprisingly, reproduction-related growth was independent of GH, ghrelin and estrogen. To determine whether these results may apply ("translate") to human physiology, data on various parameters of somatic growth were collected from women with hereditary GH deficiency. The findings indicate that GH-independent stimulation of growth by reproductive events also occurs in women.
Use of multiple animal models, rigorous characterization of GH levels in normal and GH-deficient females, and inclusion of data derived from a unique and well-characterised population of people with hereditary isolated GH deficiency and no GH replacement therapy are important strengths of these elegant and innovative studies. The results address a broader and clinically significant issue of permanent changes in body size, composition and function that result from pregnancy and lactation. This work also provides important background for further studies aimed at the identification of the mechanism involved and the role of specific reproductive events in the regulation of growth.
We sincerely thank the reviewer for this thoughtful and highly positive evaluation of our work and for recognizing its novelty, rigor, and potential physiological and clinical significance.
Reviewer #2 (Public review):
This manuscript describes the fascinating phenomenon of growth hormone (GH)-independent growth occurring in the mother during pregnancy. This growth was most pronounced in dwarf mice that are lacking the receptor for growth hormone-releasing hormone (GHRH) and therefore showing isolated GH deficiency. However, the pregnancy-induced growth could also be observed in wild-type mice, suggesting that it is a normal part of the maternal adaptation to pregnancy. The study falls short of identifying the mechanism(s) driving this pregnancy-induced growth response, but it certainly reveals a novel insight into maternal physiology. The authors have completed a range of experiments in mice to prove that, as well as being GH independent, the pregnancy-induced growth also did not require GH signaling in the liver (i.e. not another pregnancy-specific ligand operating through the GHR to promote IGF). They also provided complementary data from a population of humans with untreated isolated GH deficiency that are broadly consistent with the hypothesis. While it is important to consider the significant species differences between rodents and humans, both in terms of growth physiology and also in terms of evolution of placental somato-mammotrophic hormones, this unique population are a valuable resource and adds credence to the study. Overall, I find this a compelling research story, but disappointingly unfinished. There are some areas where additional information could improve the ability to interpret the data, and some additional concepts that could be considered in the discussion. There are also areas where additional experiments might provide important insights. However, I think that such suggestions can be considered as appropriate for future research, rather than delaying consideration of the current manuscript.
Main comments:
(1) Data in Figure 1 are remarkable - not so much the growth in pregnancy in the wildtype mice, because while elevated GH is well known in pregnancy, but growth in the dwarf mice is indicative of GH-independent growth. From these data, it seems that there is good evidence that growth in pregnancy is an adaptive function. However, it is possible that growth is achieved in dwarf mice and that in wildtype mice may have been mediated through different mechanisms. The dwarf mice showed an increase in liver and plasma IGF1, suggestive of an additional ligand driving IGF in pregnancy. One could hypothesize that such an effect could be mediated by an additional pregnancy-specific ligand activating the GH receptor. In humans, placental growth hormone could be such a ligand, but as far as we know, there is no placental GH in mice. In contrast, the wildtype animals showed suppression of liver and circulating IGF1, and low levels of pSTAT5 in the liver during pregnancy. These data (in Figure 5) are very surprising. Given the high circulating GH in pregnancy, as well as high placental lactogen (which would be expected to activate STAT5 in the liver through the Prlr), the low levels of pSTAT5 are unexpected and would seem to indicate some sort of acquired insensitivity to GH. Is this entirely driven by down-regulation of STAT5b protein, or could there be activation of other, negative regulators of STAT signalling, such as SOCS? What is causing such a profound suppression of STAT5? Regardless of the mechanism, this suggests that pregnancy-induced growth in wildtype mice is independent of circulating IGF1 (potentially a different mechanism or in addition to that seen in IGHD mice).
We thank the reviewer for this insightful comment. The mechanisms underlying the reduced hepatic STAT5b protein expression observed during pregnancy remain unknown. Previous studies have also reported desensitization of hepatic JAK2/STAT5 GH signaling during pregnancy, associated with increased expression of negative regulators of STAT signaling, including CIS (Miquet et al., Am J Physiol Endocrinol Metab 289–E607, 2005). In the current manuscript, we also observed increased Cish mRNA expression in the liver of pregnant mice. We have incorporated this information into the revised manuscript. In addition, we expanded the Discussion to acknowledge the possibility that pregnancy-induced growth may occur through distinct mechanisms in wild-type and GH-deficient mice and that, in wild-type mice, this response may involve liver-derived IGF-1-independent mechanisms.
The data shown in Figure 6 are a major strength of the study, showing that the pregnancy-induced changes are not specific to one particular transgenic model, but still occur in a variety of models affecting GH through different approaches. Given the pregnancy-specific nature of the changes, however, it seems an oversight not to have evaluated the role of placental lactogens. Prlr is highly expressed in the liver, but the function of this hormone in the liver is not well established. Could the extremely high levels of PL be mediating this growth response? Given the low expression of STAT5 in the liver and the fact that plasma IGF1 is not markedly elevated, it seems more likely that this growth response may be mediated by locally produced IGF1 in target tissues.
We thank the reviewer for this important suggestion. Although we were not able to investigate the role of prolactin receptor signaling using mouse models in the present study, we agree that prolactin may contribute to pregnancy-induced growth. Accordingly, we revised the Discussion to acknowledge this possibility and to include the potential roles of placental lactogens and locally produced IGF-1 as additional mechanisms that may underlie pregnancy-induced body growth.
I think these possibilities could be addressed by an expanded discussion of species variation in placental hormones, to highlight that humans have expansion of the GH locus, but rodents have expansion of the prolactin axis (see Soares, M. J. The prolactin and growth hormone families: pregnancy-specific hormones/cytokines at the maternal-fetal interface. Reprod Biol Endocrinol 2, 51, 2004). Importantly, placental GH and chorionic somatomammotropins (CSM) in humans are all variants of the GH gene, but CSM have preferential activity at Prlr. This seems to be a fundamental species difference in pregnancy biology, but has been interpreted as an example of convergent evolution, with conservation of prolactin and GH-like functions at the maternal-fetal interface, mediated by different mechanisms, likely contributing to the metabolic adaptations of the mother (see Newbern D, Freemark M. Placental hormones and the control of maternal metabolism and fetal growth. Curr Opin Endocrinol Diabetes Obes. 2011; 18: 409-416). While the preceding function has focused on explaining the evolution of placental lactogens (either prolactin or GH variants), the present data suggest that there are also mechanisms to maintain growth in pregnancy, independent of GH (even in the absence of a placental GH).
Thank you very much for this observation and suggestion. In the Introduction, we succinctly mention species-specific differences in the GH locus (see Introduction). Since our study focused primarily on mice, we believe expanding on this information would detract from the study's focus, especially given that such details are available in other publications. However, we have added a sentence to the discussion noting that, despite significant species-specific differences in the GH locus, there has been evolutionary conservation in the maintenance of pregnancy-induced growth, potentially involving distinct mechanisms in rodents and humans, though both appear to be GH-independent.
“However, important differences are observed between humans and rodents. Humans, but not rodents, possess the GH2 gene, which encodes the placental growth hormone (GH) variant, whose production progressively replaces pituitary GH (derived from the GH1 gene) secretion during pregnancy (Liao et al., 2018). In contrast, rodents maintain pituitary GH secretion throughout gestation (Gatford et al., 2017; Liao et al., 2018). Additionally, human GH, both pituitary and placental variants, as well as chorionic somatomammotropins, can activate both the GH receptor (GHR) and the prolactin receptor (PrlR), explaining their lactogenic effects. In contrast, murine GH activates only the GHR (Bartke and Kopchick, 2015).”
(2) The human data are very interesting, and my initial impression was that it seemed unlikely to be the same phenomenon. Was there any real evidence for "growth" in pregnancy? Pubertal maturation of long bone growth might be expected to prevent further growth in adulthood. However, these issues were appropriately discussed, and it seems well justified to evaluate this unique population of women with IGHD who underwent pregnancy. It would be very interesting to know if these women experienced elevated IGF1 during pregnancy, indicative of placental GH contributing to growth. Mechanistically, this might be more like the dwarf mouse situation of IGHD, that the situation in wildtype mice (associated with liver insensitivity to GH and low IGF1).
We thank the reviewer for this comment. Unfortunately, the pregnancies of the women with IGHD occurred with limited medical assistance, and no additional clinical information is available, particularly regarding changes in circulating IGF-1 levels during pregnancy. Therefore, the evidence presented and discussed in the current manuscript represents the only information currently available on pregnancy-induced growth in this unique population.
(3) It would be useful to include investigations that isolate the effects of pregnancy and the placental hormones. Such studies could include evaluating growth in pseudopregnant mice with IGHD (pregnancy-like changes in hormones but lacking the placental contribution) and in IGHD animals that experience pregnancy but not lactation (pups removed at birth). I accept that this might be too large an additional study to add for the present manuscript.
We thank the reviewer for this valuable suggestion and agree that this experiment could provide valuable information regarding the role of placental hormones in pregnancy-induced growth. Interestingly, previous work has shown that female mice housed with vasectomized males exhibit increased body weight compared with non-reproductive females, although this increase is substantially smaller than that observed in females with successive litters (Garratt et al., Proc Natl Acad Sci U S A 117:15748–15754, 2020). We discuss this study in the current manuscript. However, this study did not provide additional information on whether this increase reflects greater adiposity, enhanced body growth, or both. Unfortunately, we are unable to perform these time-intensive experiments. We appreciate the reviewer's understanding and agree that this important question should be addressed in future studies.
(4) It is an important and translationally relevant observation that pregnancy increased the risk of long-term weight gain, and that after the first pregnancy, the pregnancy-induced growth response was more directed to promoting fat deposition. Does this provide any mechanistic insight? Could a metabolic adaptation result in growth?
We thank the reviewer for this thoughtful comment. At present, we do not have additional data to explain the mechanisms underlying the pregnancy-induced increases in body growth and adiposity or to determine whether these processes are mechanistically linked. In the revised manuscript, we have expanded the Discussion to address potential mechanisms that may contribute to the observed post-pregnancy growth, including hormonal and metabolic factors, while acknowledging that these possibilities remain speculative and require further investigation.
Reviewer #3 (Public review):
Summary:
The study describes an increase in body growth and body composition in both mice and women. In mice, the impact on growth is mainly seen during the first pregnancy, and the changes postpartum on body composition are also different during the first and second pregnancies. The study has used various knock-out models in the growth hormone axis to understand these changes as well as some gene expression analysis related to GH, IGF-1 and estrogen signalling pathways.
Strengths:
(1) The inclusion of various knock-out mouse models that allow for exploration of mechanisms related to the above-mentioned changes.
(2) The investigation of gene expression of GHR, IGF-1R and ER pathways.
Weaknesses:
The human findings are dependent on the patient's recollection of bodily changes after their pregnancies.
Conclusion:
The authors have partly achieved their aim of describing changes in growth and body composition that remain after pregnancy and the mechanisms behind these changes. This study may have importance for a wide variety of research areas as well as in the clinical setting. The study is also unique in its attempt to bridge findings in mice to a unique human model of congenital GH deficiency.
We sincerely thank the reviewer for the thoughtful evaluation of our study, for recognizing its novelty and potential significance, and for highlighting the strengths of our experimental approach. We have revised the manuscript to further acknowledge the limitations of the human data, as suggested.
Recommendations for the authors:
Reviewer #1 (Recommendations for the authors):
The findings presented in this study are novel, exciting and important. I believe it would help the readers to include a diagram showing the timing of the various measurements and tissue collection in relation to conception, parturition and weaning. It would also be helpful to expand the discussion to include the author's thoughts on the possible role of various placental hormones, pituitary prolactin, metabolic changes and/or other factors in the observed growth. Finally, humans from whom the data were obtained should probably be referred to as individuals or subjects rather than patients.
We thank the reviewer for these helpful suggestions. We included Figure 7 in the revised manuscript, which summarizes the study's experimental timeline. Additionally, we expanded the Discussion as recommended and replaced the term "patients" with "subjects" throughout the manuscript.
Reviewer #2 (Recommendations for the authors):
In addition to my comment above about addressing the different evolution of placental hormones, the following minor suggestions are provided:
(1) Abstract line 23 "most" could be "some" (because lots of evidence that pregnancy-induced adaptations are long-term - e.g. brain structure, maternal behavior, endocrine changes) - see below.
Done.
(2) Is "reproductive experience" the best term? Or is it "pregnancy"? (likely specifically due to the presence of placental hormones and/or maternal patterns of hormones, rather than other aspects of "reproductive experience) e.g. mating, parturition or lactation?
We appreciate the reviewer's point. However, because we cannot exclude potential contributions of mating, parturition, or lactation to the observed increases in body growth and adiposity, we prefer to retain the term "reproductive experience," as the mice in the present study underwent all of these processes rather than pregnancy alone.
(3) Potentially, the introduction could add references to brain changes in humans in pregnancy (this is a particularly topical area of research where long-term changes have been reported; e.g. Pritschet L, Taylor CM, Cossio D, Faskowitz J, Santander T, Handwerker DA, Grotzinger H, Layher E, Chrastil ER, Jacobs EG. Neuroanatomical changes observed over the course of a human pregnancy. Nat Neurosci. 2024 Nov;27(11):2253-2260; Martínez-García M, Paternina-Die M, Barba-Müller E, Martín de Blas D, Beumala L, Cortizo R, Pozzobon C, Marcos-Vidal L, Fernández-Pena A, Picado M, Belmonte-Padilla E, Massó-Rodriguez A, Ballesteros A, Desco M, Vilarroya Ó, Hoekzema E, Carmona S. Do Pregnancy-Induced Brain Changes Reverse? The Brain of a Mother Six Years after Parturition. Brain Sci. 2021 Jan 28;11(2):168. There is also a significant literature on long-term effects of reproductive experience (Bridges RS. Long-term alterations in neural and endocrine processes induced by motherhood in mammals. Horm Behav. 2016 Jan;77:193-203).
We thank the reviewer for this helpful suggestion. Accordingly, we incorporated these references into the Introduction to further emphasize the long-term effects of reproductive experience.
(4) Figure 1: Why show body weight as a "delta" for primiparous animals, and "absolute "values for multiparous? Similarly, it seems that body length is an informative readout for these experiments, but this is only reported for one model, and most models are only shown as body weight and lean mass.
We thank the reviewer for this comment. For the primiparous mice, we chose to present the change (Δ) in body weight and lean mass because it more directly illustrates the effects of the first reproductive experience relative to each animal's baseline while avoiding redundant presentation of both absolute and Δ values, as both analyses yielded the same statistical conclusions. For the multiparous mice, absolute values were presented to facilitate comparison with the corresponding images and to allow direct comparison of body size between wild-type and Ghrhrlit/lit mice. Regarding body length, these measurements were collected only in the multiparous cohort and were not obtained after the first reproductive experience. Therefore, we are unable to provide body length data for the primiparous groups.
(5) It seems it would be better to present all of the mouse data first, then the supporting human data.
Done.
(6) The manuscript includes a high-quality investigation of GH secretion - particularly the pulsatile secretion of GH. Is it possible to have matching IGF data (at least multiple time points in pregnancy)?
We agree with the reviewer that serial measurements of circulating IGF-1 during pregnancy would provide valuable additional information. Unfortunately, this analysis is not feasible because the limited blood volume collected during the study did not allow sufficient sample storage for additional measurements.
(7) Line 221 - "GHRH signaling is required for pregnancy-induced increases in GH secretion...". Can you actually make that conclusion, or is it possible that the lack of GHRH developmentally has permanently altered the pituitary gland, so it cannot respond to other GH secretagogues?
We thank the reviewer for this important comment. We agree that the congenital absence of GHRH signaling may cause developmental alterations in the pituitary that impair the response to other GH secretagogues. Therefore, we cannot distinguish whether the lack of pregnancy-induced increases in GH secretion reflects the absence of GHRH signaling per se or the developmental defects resulting from GHRH deficiency. We removed the aforementioned phrase from Results and have revised the Discussion to acknowledge this important limitation and to clarify that the observed phenotype may be secondary to impaired pituitary development.
(8) Line 238 - "GHR signaling stimulates hepatic insulin-like growth factor 1 (IGF-1) secretion, particularly by activating the signal transducer and activator of transcription 5b (STAT5b) pathway" for this point, should probably cite: Davey HW, Xie T, McLachlan MJ, Wilkins RJ, Waxman DJ, Grattan DR. STAT5b is required for GH-induced liver IGF-I gene expression. Endocrinology. 2001 Sep;142(9):3836-41.
Thank you for this suggestion; we added this reference.
(9) Line 240 - "GH action in the liver is not only controlled by the pattern of GH secretion...". should probably cite Waxman's work regarding patterns of GH secretion (e.g reviewed in Waxman DJ, O'Connor C. Growth hormone regulation of sex-dependent liver gene expression. Mol Endocrinol. 2006 Nov;20(11):2613-29.).
This reference was included in this sentence.
(10) Methods: Check statistics - some of the analysis should have been repeated measures?
We thank the reviewer for this comment. We carefully re-evaluated all statistical analyses and did not identify any experiment for which a repeated-measures analysis would have been appropriate. Therefore, no changes to the statistical analyses were necessary.
Reviewer #3 (Recommendations for the authors):
(1) Introduction: The context of the sentence "Furthermore, historically, females have been underrepresented in studies" is unclear.
We thank the reviewer for this observation. Our intention was to emphasize that, because pregnancy is unique to females and females have historically been underrepresented in biomedical research, pregnancy-related physiology has received comparatively less attention. However, we agree that this statement was not essential in this context. Thus, we have removed it from the revised manuscript.
(2) Introduction: Based on the paper, the main aim seems to be to study the lasting effects of pregnancy on the mother and not primarily to study the hormonal changes during pregnancy.
We thank the reviewer for this helpful observation. We agree that our study primarily focuses on the long-term effects of pregnancy on the maternal organism rather than the hormonal changes that occur during pregnancy. Accordingly, we revised this sentence to better reflect the main objective of the study: “Therefore, the goal of this study is to investigate the lasting effects of pregnancy on the maternal organism and the possible involvement of the somatotrophic axis in these changes.”
(3) Other endocrine factors could affect the changes seen after pregnancy in mice and humans, such as the insulin level and activation of the IR.
We thank the reviewer for this valuable suggestion. In the revised manuscript, we expanded the Discussion to acknowledge the potential contribution of several endocrine factors, including insulin signaling, to pregnancy-induced growth.
(4) The receptor activation in tissues other than the liver has not been studied, such as in the growth plate, adipose tissue and muscle.
We thank the reviewer for this important comment. We agree with this point and have addressed this possibility in the revised Discussion.
(5) Information on the age of the patient at the time of pregnancy could be included as well as the patient's height and weight before pregnancy and at follow-up.
This information was added as Table 1.



